



When you’re trying to understand what’s going on with your hormones, it’s really tempting to zero in on one single lab result. Maybe your testosterone came back high, your fasting insulin looks “normal,” or you’ve been staring at your LH and FSH numbers trying to figure out what they mean. But with PMOS, one number rarely tells us the whole story.
Polyendocrine metabolic ovarian syndrome (PMOS), formerly called polycystic ovary syndrome (PCOS), isn’t just an “ovarian” condition. It’s a complex hormonal and metabolic condition, which is why it’s important to look at your hormone levels and metabolic markers together rather than treating each lab result like a separate piece of information.
I’m a Registered Dietitian specializing in PMOS who has the condition myself. I was handed the same advice you’ve probably been offered: lose weight, work out, cut calories, and go on birth control. So in this guide, I’ll walk you through what hormone levels mean with PMOS, what they can tell you, and why context matters.

PMOS Hormone Levels: What They Are and Why They Matter
One thing I want women with PMOS to know is that there isn’t one single hormone level that tells you whether or not you have the condition. It should be looked at alongside your symptoms, your history, and a full clinical assessment. I’ve said it before and I’ll say it again: avoid honing in on ONE single result, it won’t tell you much by itself. Focus on the patterns across hormones and markers, and how that pattern lines up with what you’re feeling.
Here are some of the hormones you may hear most about when looking at PMOS as a whole:
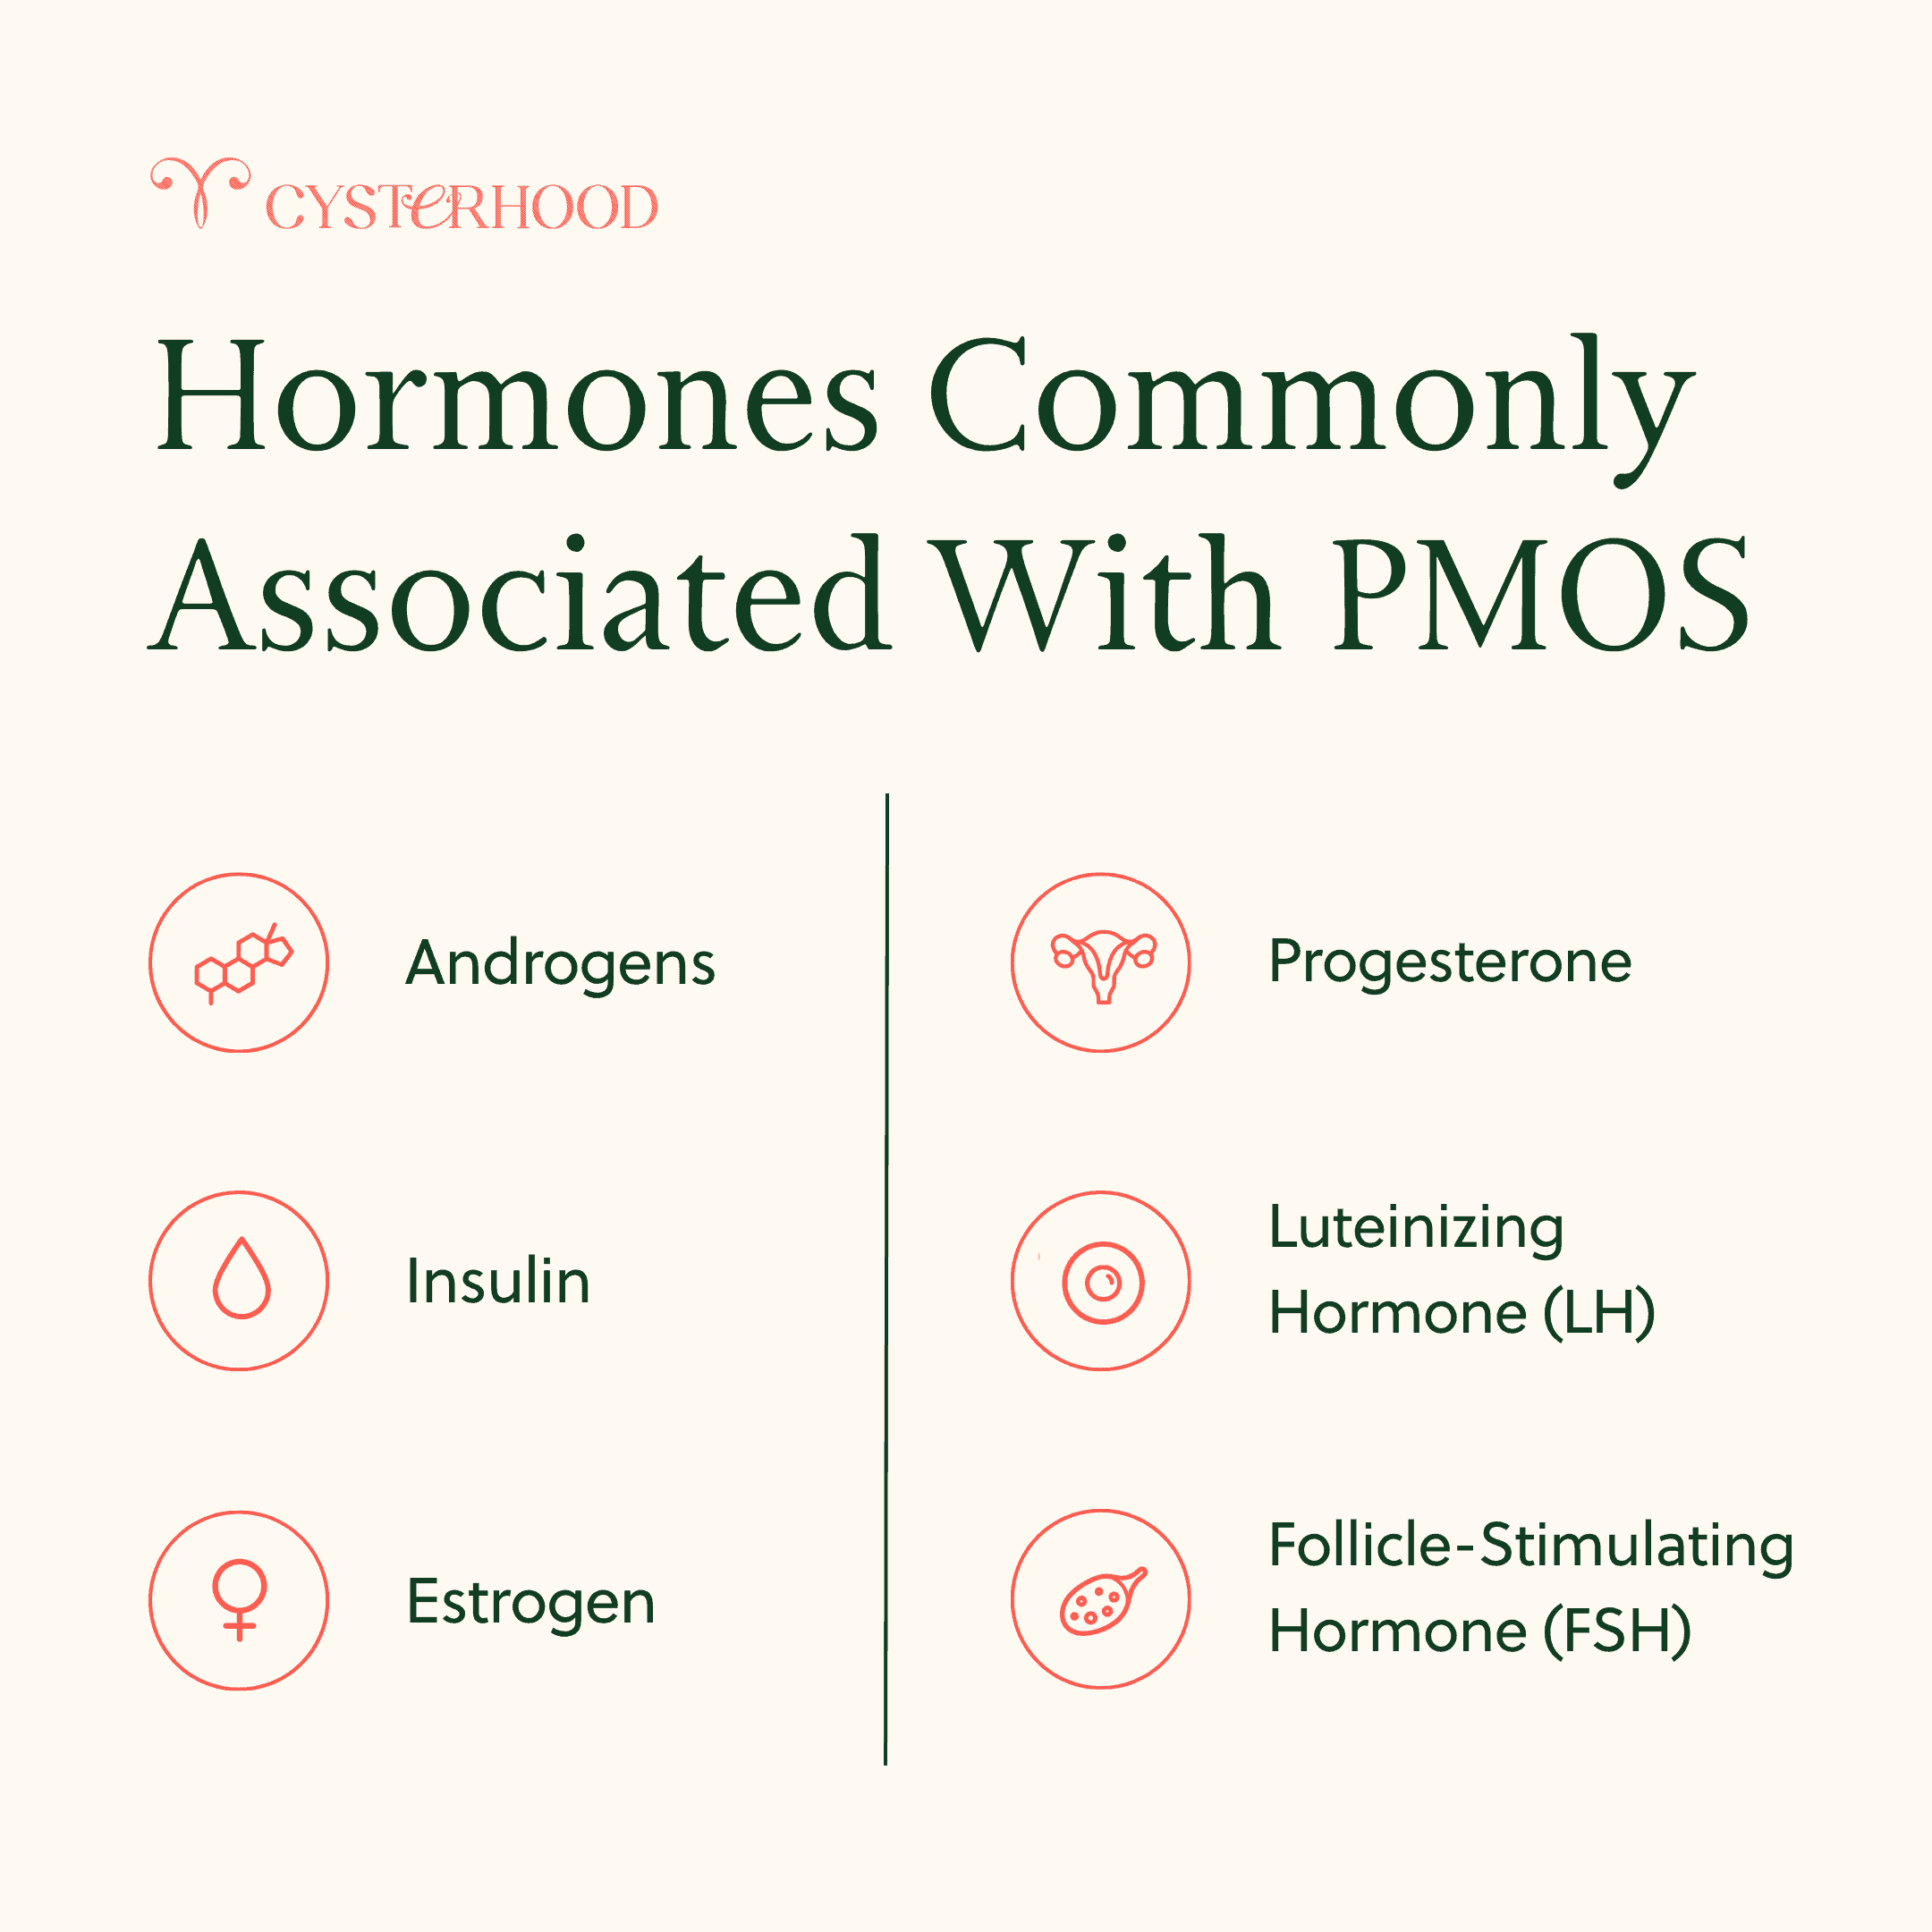
What Hormones Are Associated With PMOS?
Androgens, insulin, and reproductive hormones can all be part of your PMOS picture, and changes in these levels can help explain some of the symptoms you’ve been dealing with.
Androgens
Androgens are often called “male hormones,” but women naturally produce them too. With PMOS, levels can be higher than expected, particularly testosterone and DHEA-S. This is generally where you’ll hear doctors use the term “hyperandrogenism,” one of the hallmark features of PMOS.
Higher androgen levels can show up as symptoms you may already be familiar with, like excessive hair growth (in all of the places you don’t want it), acne, and for some women, hair loss on the scalp. And for some women, even if their bloodwork isn’t dramatically elevated, they can still have noticeable symptoms. This is often why your provider will look at your lab results as a whole and combine them with symptoms you’re experiencing.
Noticed increased body hair and stubborn, aggravating acne for a while now and are wondering how to lower testosterone? I cover the “hows” and “whys” more in-depth in my guide on PMOS (PCOS) high testosterone symptoms.
Insulin
Insulin helps move glucose from your bloodstream into your cells so your body can use it for energy. With PMOS, the problem is that the cells don’t respond to insulin as well as they should. Your body makes up for it by producing more insulin.
Over time, higher insulin levels can also signal the ovaries to produce more androgens. That’s why insulin resistance can be connected to symptoms of PMOS that don’t really seem related to blood sugar at first, like irregular periods, increased cravings, and difficulty with what feels like persistent weight gain.
No, insulin technically isn’t a reproductive hormone, but we still want to pay attention to it when we’re looking at the bigger hormonal picture with PMOS.
Reproductive Hormones
Estrogen, progesterone, LH, and FSH all play a role in your menstrual cycle and ovulation. For women with PMOS, these hormones may not follow the patterns you’d typically expect throughout the cycle, especially if ovulation isn’t happening “normally.”
You may experience irregular periods, long stretches between menstrual periods, or, sometimes, no period for months. If you’re not ovulating regularly, your body may also produce less progesterone because progesterone normally rises after ovulation.
And what about the “cysts” associated with PMOS? Despite the original name, these aren’t actually ovarian cysts. They’re small, immature follicles that can be seen on an ultrasound when the ovaries aren’t regularly releasing an egg.
This is why your provider won’t look at your reproductive hormones alone. Your androgen levels and metabolic markers, including insulin, can also help them understand what’s going on in your cycle.
The Metabolic Side of PMOS
One thing that’s important to understand about PMOS is that it isn’t only about your ovaries. It’s metabolic, which is exactly why the name is polyendocrine metabolic ovarian syndrome and reflects more than what’s happening in the ovaries alone.
Insulin resistance is a big part of the picture for people with PMOS. When your body has trouble using insulin well, your insulin levels may rise to compensate. Higher insulin can also affect androgen production and contribute to some of the symptoms you experience.
The metabolic markers worth knowing about include your blood sugar, along with markers that can help your provider assess your metabolic health and risk for conditions like type 2 diabetes and high blood pressure. These are important to keep an eye on over time, especially if you have insulin resistance.
Knowing what’s happening metabolically can give you and your provider more information to work with. Instead of looking at periods or hormone levels as a completely separate issue, you can slowly start to see how they’re actually connected.
What Do PMOS Hormone Levels Mean for Diagnosis?
This is where I want to be really clear. Hormone testing is one part of assessing PMOS, and no single result confirms it or rules it out. Two women can have very different labs and both have PMOS, because the condition shows up as a pattern, not a single flag.
That’s also why you can’t diagnose yourself from one hormone alone. A slightly elevated result on its own doesn’t mean much, and a “normal” result doesn’t automatically clear you either. Bring your labs to a provider who can look at your symptoms, your cycle history, and, if necessary, an ultrasound as one picture rather than individual parts.
If you’re navigating specific findings, it can help to understand how to reduce AMG levels in PMOS when AMH is part of your workup. When you know more about the condition, you gain your power back.
Want a clearer starting point for your own symptoms? Take my free PMOS quiz and get pointed toward what to focus on first.

How to Support Healthy Hormone Levels With PMOS
As someone with PMOS myself, I know what you’re feeling right now may feel overwhelming, confusing, or honestly, kind of heavy. But here’s the silver lining: PMOS doesn’t have to get the final say. A gluten- and dairy-free diet, low-impact movement, quality sleep, paying attention to your mental health, and stress management techniques can all help support more balanced hormone levels over time. This isn’t an overnight fix, and I’d never promise you one. It’s a steady, consistent way to address symptoms at the root.
Give this time. I always say it takes about 3 months to change the picture of your ovaries, so think in cycles, not days. For meal plans, PMOS-friendly meals, slow-weighted workouts, and a community of women doing this alongside you, download The Cysterhood App. It’s the whole method in one place, built by people who actually have PMOS.
And if you’re not ready to dive in yet, start with the free PMOS quiz so you know where to begin.
You’ve got this,
Tallene, RD
Medical disclaimer: This content is for educational purposes only and is not medical advice. It is not intended to diagnose, treat, cure, or prevent any condition. Always talk to your doctor or a qualified provider about your hormone levels, your symptoms, and any changes to your medications, treatment, or care.